
Most (all?) of the side effects you're currently experiencing are likely coming from the CJC-1295. I'm assuming you have a blend? You can run Ipamorelin solo and get benefits. Might be worth a try to pick up a single vial when you make your next group purchase and experiment.
N
Neil McCauley
@Neil McCauley

Posts
-
Peptides, Anaphylactic Shock & Epi Pens -
Peptides, Anaphylactic Shock & Epi PensI appreciate the warning and bringing it up again. I initially thought that it would just be a risk early on or that it wouldn't suddenly jump to anaphylaxus. Unfortunately for allergies its often the case that you're good until you very suddenly are not. There can be warnings, but there could also be none, or too subtle.
The flush from CJC is a warning, its a weak histamine response. Mine became really low level after the first week, but it was still my body telling me something was not quite right. Add to the fact that my nearly nonexistent asthma was acting up even slightly... It's just out of what I consider worth the risk, especially since it's fourth or fifth on my list of health priorities.
Might still get an epi pen in case I get a bad batch of Tirz, Wolverine or Klow, but those don't generate constant histamine responses (the flush) for me and are much higher in my priority list.I don't blame your caution whatsoever, and given your history, best to be prudent. However, I think it's worth reiterating his age and comorbitities, and the fact that he was taking twice the prescribed dosage.
To put this into context, I asked A.I. to give me a rough estimate at what % of commonly prescribed pharmaceutical drugs, when taken at double the prescribed dosage over time, would lead to serious side effects and possibly death.
"Rough guess: ~15-25% of commonly prescribed systemic drugs have a realistic path to death under sustained 2x dosing in a typical patient. Serious non-fatal harm (organ injury, arrhythmia, bleeding, severe hypoglycemia) would be maybe 35-50%"
Given, this is across a general population as well, not a cohort of individuals aged 75+ with priors (like the aforementioned individual in question), which would likely dramatically increase those percentages.
I'm not saying peptides are perfectly safe and harmless, just trying to add some context and nuance. All drugs interventions do carry some risk.
-
Peptides, Anaphylactic Shock & Epi Pens@TrueNorth he suffered from Asthma and hypertrophic cardiomyopathy. Motsc and CJC both can cause a serious histamine reactions if you have these conditions it can be much worse. Seems like we are getting half the story on this one. If you suffer from a condition like the ones he had you need to be extra careful. Certainly have an epi pen nearby. The conditions he had was the perfect storm it appears
He was taking double the prescribed dosage as well
-
Nutritional ketosis and fat mobilizing peptidesYou want to pull as many levers as you reasonably (and safely) can. Yes to a lower carb diet. Yes on Tesa. Yes on a GLP.
I would actually advocate for a GLP over AOD for recomp/fat loss if you're looking for something to stack with Tesa. If you already have AOD that's fine obviously use it, remember its 4-6 weeks max before massive desensitization occurs.
If you're new to the GLP game I'd try Tirz first before jumping to Reta. As always, start at the very low dosage. You may end up only needing that.
Remember hormones are the foundation and paramount to keeping fat off long term. Make sure to get a panel ran and that the big ones are at least in a mid range level.
-
RFK Jr. Removes Restrictions On Unapproved Peptide InjectionsThis does nothing for us unless you want to find someone to prescribe and then pay insanely high prices from a compounding pharmacy. Correct me if I am wrong.
In the marijuana industry when it became legal and sold in retail, the black market prices came down drastically. I wonder if similar market forces will be in play.
-
No knee replacementAre you on any forms of HRT? Hormones, notably testosterone, growth hormone and DHEA, are paramount to overall joint health.
Since you're 73, I'd start there, if you haven't already, before trying anything else.
-
Tesamorelin cycling@neil-mccauley do you think 500mcg tesa/250mcg ipa separately w tesa am ipa PM would be a good starting range?
Do them both at same time. Ipamorelin is going to suppress somatostatin tone which will help not only increase the GH pulse from Tesa but also extend the pulse tail, thus resulting in more GH released. Separating them destroys the synergy, and is just more work, more pinning, more supplies, etc.
I'd use a much lower dosage of Ipamorelin to start too. If you have the 10/3 blend, that's going to be 500mcg/150mcg. 150 seems low, but remember receptor saturation point starts at 1mcg/kg, so thats double that amount. If you're pulling them out of separate vials, I'd go 500/100.
Remember, the higher the Ipa dosage the faster/more receptor desensitization will occur (and probably the same can be said about antibody build-up with Tesa). So it really is important to use lower end dosages and use outside methods to help things work synergistically.
This is why I think really being strict about your fasted windows is hugely beneficial (3 hours prior/2 hours after). This will help amplify response and lesson the need for ever increasing dosages. Also, utilizing a 30 day cycle break after 90 days. Exercise is huge, as it lowers fasted insulin/glucose, again, allowing for a more favorable GH response. I think eating a higher protein, less junky carb diet and staying away from all day grazing/snacking and tightening up meal windows with no snacking in between is critical. So is DHEA supplementing if levels are < 300 (improves insulin sensitivity and helps restore GH pulse via several mechanisms).
-
Tesamorelin cycling@BeeKind Good question, I wonder how much it can help versus just Tesamorelin. Maybe it can allow to use a lower dose of Tesa, for example instead of 1.5 mg a day use 1.0 mg + 0.2mg Ipa (I just guess the numbers) to get the same IGF1 boost with less Tesa side effects, also a bit cheaper. The trade-off is that you have to make pauses with Ipa.
Your thinking is correct here regarding using Ipamorelin "to get the same IGF1 boost with less Tesa side effects, also a bit cheaper". You need to make pauses with Tesa too (see my responses above about antibody build-up over time).
But I'm with you, I think the doses most are using with Tesa are exceedingly too high. Everyone's basing it on the clinical research using 2mg, but remember, that was based on a sick cohort of users who also were using outdated, less effective methods who needed that kind of dosing to overcome their obstacles. What were they? Multiple comorbitities including HIV, weren't pinning it around fasted windows, didn't pair it with Ipamorelin, and very likely weren't health conscious fitness people.
I suspect that if you correct the mistakes made in the trials with more advanced protocols and a healthier user base, the dosages needed for a favorable response are much, much lower than the 2mg used. Pairing it with Ipamorelin, I'd start with 500mcg and adjust up from there.
-
Tesamorelin cycling@vpeps @beekind I started with a Tesa/Ipa cycle but stopped the Ipa part after 2 weeks. I didn't like the way I felt (suspect is was mostly water retention) and decided it was either the Tesa or Ipa or both. I stopped the Ipa (and the side effects went away) but have continued the Tesa on the same 5/2 schedule. I feel much better on just the Tesa and decided to extend that cycle to 16 weeks. That has been my experience, but your mileage may vary.
It wasn't the Ipamorelin. It was too high of a dosage of both causing the water retention, a side effect of excessive GH levels. Ipamorelin makes Tesa work that much better. Stopping the Ipa just lowered your GH levels enough to reduce the side effects from GH. You'd be better off actually taking less Tesa, because its not only the one moving most of the load here, it's also a lot more expensive (and comparing the two, has more side effects, like antibody build-up, which Ipamorelin doesn't seem to have).
As far as your 5/2 cycle protocol, it's not the most effective way to go about it, see above and my posts in this thread.
-
Tesamorelin cyclingIt's been run for more than a year before.
From my understanding, it's only cycled when you do a Tesa/Ipa blend [Tesa+] because it's the Ipamorelin that needs 5 on 2 off, alone Tesa is 2mg 7 days a week.
https://www.peptideprotocolwiki.com/peptides/tesamorelinCurrently I do Tesa+ [2mgTesa/5mgIpa] nightly on weekdays, 2mg Tesa on the weekends.
I'm currently on my second cycle of this, took a month off completely of Ipo but kept the Tesa flowing.I'v had great results [but I'm also running Reta]
I eat whatever I want as long as it stays under 2300 calories and hit my protein goals.
I just had 2 double cheeseburgers and steak fries for lunch [1300calories]. Combined with the egg white omelette for post workout breakfast and a protein shake tonight [4 hours before my Tesa dose, it's supposed to be taken fasted] I will be at 2,093 calories 200g of protein, 93 fat, 103carbs.As EVERYONE would wisely tell you, take this with a grain of salt.
I'm no doctor and don't advise you to follow in my footsteps, just telling you my protocol.Ipamorelin needs a full 30 days off cycle in order for full complete receptor reset. Tesa likely (further research needed) needs a full 30 days off as well to help prevent/mitigate antibody build-up.
The whole 5/2 cycle guideline for all GH peptides (including HGH) needs to be thrown out completely. It's based on faulty, anecdotal data and mostly came from the bodybuilding community just using it as a way to save 15% on HGH costs over time.
2 days does nothing to reset receptor sensitivity or prevent antibody build up. You need a full 30 days minimum for that. Not only that, it will lead to less potent peptides over time because peptides do lose potency every day post reconstitution. There is no reason to have a reconstituted GH/HGH peptide sitting around for 2 days, losing potency, going unused.
This is a great read
https://www.realpeptides.co/tolerance-ipamorelin-cycling-research-protocols/
"Pulsatile dosing within cycles (5 days on, 2 days off) delays but does not prevent receptor downregulation, making macro-breaks more effective than micro-breaks"
"Complete receptor recovery requires 28–35 days of washout, supporting the 4–6 week off-period standard in empirical research protocols"
"Tolerance to ipamorelin cycling develops when GHSR-1a receptors in the anterior pituitary undergo ligand-induced downregulation after 8–12 weeks of continuous peptide exposure. Receptor density decreases by 35–50%, reducing GH pulse amplitude even when peptide concentration remains stable. Structured off-periods of 4–6 weeks allow receptor resensitization, restoring baseline response to subsequent cycles"
-
Tesamorelin cyclingOne of the reasons for cycling off Tesa isn't due to receptor sensitivity but to prevent antibody buildup which did occur in 50% of patients with recurring 52 week treatment.
Antibodies were mostly non-neutralizing, with no apparent effect on IGF-1 response or efficacy, however there's no long term clinical data on that beyond a year.
So to be on the safe side, I'd cycle off for 30 days until more research is done. I'd also always use Ipamorelin alongside Tesa anyways, so you're going to need to cycle that anyways.
-
Nexaph - Tesamorelin/Ipamorelin purityI noticed Aavant's latest Tesa batch also sits at 97% purity, Janoshik COA.
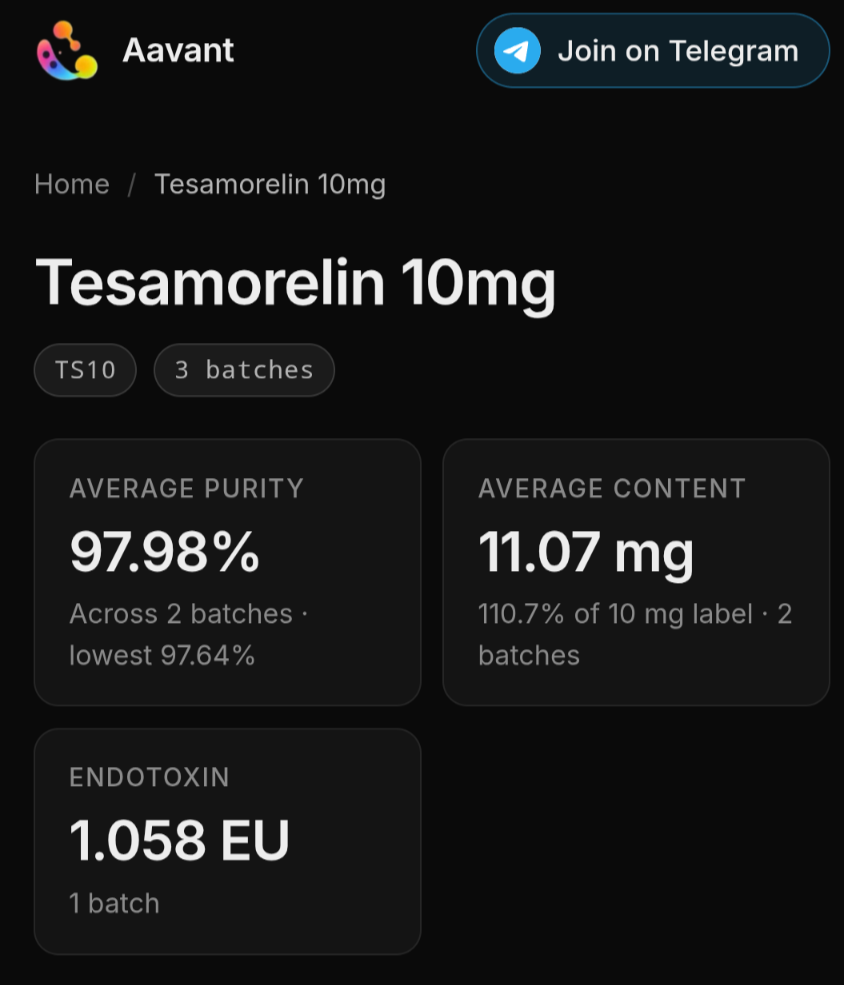
97.98 average purity, I'd call that 98.
I have heard that Tesa, at 44 amino acids, is much more difficult to manufacture than the other GHRH analogs which are 29, and therefor results extra broken proteins which will affect the purity and make hitting 99%+ more difficult.
This leads to a potency issue. Now I certainly wouldn't want something in the 96% range or lower, a 97.98 average purity is probably on par with what everyone's been using this whole time, and those COAs claiming 99%+ were mostly doing less effective testing protocols.
-
What peptide for weightloss won’t make my RHR jump@ResearchCat I don't like CJC-1295, it severely destroys my sleep. But I do lose weight on it, and quickly, especially belly fat.
Pin fasted, first thing a.m. Wait the full 2 hours after administration before eating. It will be long gone from your system when its bedtime (given its no DAC)
This is what I do. Works much better for me than evening. I have friends who swear GHRH makes them sleep better but I don’t get that benefit. and fasting at night is almost impossible for me.
At the end of the day, total time under the curve/total GH output is what matters (and what works for you that's convenient and allows consistent use). There are tons of people in the bodybuilding community who pin HGH fasted morning/afternoon or multiple times per day who get incredible results that only reinforces this theory.
-
What peptide for weightloss won’t make my RHR jump@Neil-McCauley I tried that. This trick works with Tesamorelin, but CJC-1295 does bad things to my sleep, even at 0.15 mg, even if used in the morning. Ipamorelin does not affect my sleep.
You can try a much lower dose than 150mcg. The clinical data has shown a favorable response and receptor saturation point at 1 mcg/kg.
-
What peptide for weightloss won’t make my RHR jump@ResearchCat I don't like CJC-1295, it severely destroys my sleep. But I do lose weight on it, and quickly, especially belly fat.
Pin fasted, first thing a.m. Wait the full 2 hours after administration before eating. It will be long gone from your system when its bedtime (given its no DAC)
-
What peptide for weightloss won’t make my RHR jump@Neil-McCauley doesn’t tesa only hit visceral fat
An important distinction is that tesa is the only GHRH that is specifically tested/proven to reduce visceral fat as that is what it was developed for. Other GHRH may also (probably do) reduce visceral fat along with other fat, but nobody is going to spend billions to do clinical research on it if they can’t monetize it.
I have researched sermorelin, tesa, and CJC/Ipa and haven’t seen a meaningful reduction in visceral fat. That being said, I haven’t done more than 60 days at a time, which is on the very low end of what you need to do in order to achieve results with either sermorelin or tesa.
If i researched tesa again, I would probably research 1mg/day x 180 days, maybe with a checkpoint at 120 days. (Maybe tesa/ipa, TBD for 2027.)
By comparison, I notice muscular changes with CJC/IPA in 4-6 weeks - which is why everyone loves it.
Agree with all of that. Tesa does have a slightly longer half life with the extra 15 amino acid structure in place which may (likely) aide in slightly more pronounced fat burning effect. For me personally I have had such positive effects with CJC-1295 that the cost/benefit ratio perhaps sides with CJC-1295, however if someone is new to both and specifically is looking for fat loss and money isn't an issue I don't see any reason why not to try Tesa first.
I would also pair either of the above with DHEA (if levels are < 300) for an increased fat burning effect.
I have extensive research with CJC-1295. My research with Tesa is limited to very recent, so I am also relying more on clinical data and online anecdotal experiences.
As far as your lack of fat loss, you have to track your macros. There's no way around it. You have to be in a calorie deficit. Boosting fat loss via GHRH and caffeine will only go so far, it's merely a couple of levers, you have to cut the calories down.
I have found the best diets generally prioritize protein, whole single ingredient foods with periods of short intermediate fasts, like 4 to 8 hours. I don't think you want to fast for extensive periods of time but you really want to avoid all day grazing which will chronically elevate insulin and suppress GH levels.
-
What peptide for weightloss won’t make my RHR jump@Neil-McCauley doesn’t tesa only hit visceral fat
All fat.
A morning fasted dosage of Tesa/Ipa + Caffeine (pill or black coffee) is going to be the best fat burner in terms of effectiveness versus side effects that you're going to find.
You fast a good 4+ hours and do some cardio and actually track your daily macros you will blast away fat.
The people in the Tesa trials lost weight and they had everything going against them. Multiple comorbitities including HIV, weren't fasting, didn't pair it with Ipamorelin, likely weren't health conscious fitness people and despite all those obstacles saw incredible results.
Imagine what someone could do if they pinned fasted, added Ipamorelin, coupled that with caffeine, did morning fasted cardio and tracked their macros, as well as weren't suffering from the effects of HIV.
-
What peptide for weightloss won’t make my RHR jumpTesamorelin
-
Beyond the Scale: What Has Reta or Tirz Changed for You?@jackiee said:
She had a patient with a weight issue and rheumatoid arthritis that eventually settled on a 2.5 mg dose once a month. That dose relieved 90% of her RA symptoms, and pulled her life out of pain territory.
That's pretty incredible. Has anyone else heard/experienced anything similar?
Obviously a combo of both, but I wonder what % of the results are anti-inflammatory effects of the drug versus just sheer weight loss having a positive effect on RA.
-
Tesamorelin/Ipamorelin and Huperzine A for somatostatin inhibitionyou're better off just taking more Ipamorelin
Is more Ipa better? I was under the assumption 500mcg was the max does... not sure where I picked it up from.
Yeah I think so, at least up until a point. I just don't think those OTC oral add ons are going to add any value onto what you're trying to do (inhibit somatostatin). I think with 300 - 500mcg of Ipamorelin that lever is already pressed down as far as it's going to go, and adding anything on to that simply isn't going to move the needle in any positive direction worthwhile. That's the end result I was really left with trying to experiment with OTC orals as an add on.
Remember, all these orals do add on to total hepatic load, and they aren't completely without side effects themselves. I think that if Ipamorelin was some really expensive, exotic/rare peptide and/or had strong side effects at higher doses and you were trying to minimize costs/sides, it might be something worth looking into, but heck Ipa is pretty cheap nowadays and is actually comparable in price to other OTC compounds that do similar actions.
Now where I do think that perhaps they might be an interesting case use would be to use while off cycle.