
I ain't upset that Nexaph overfills its vials a tad
N
Neil McCauley
@Neil McCauley

Posts
-
Lab vs Lab, We tested 5 Labs using the same Kit. -
Show off your swag!
-
YouTube Killed Randy?Rumble is awesome and I've been on there for awhile now. I ended up on there when a lot of my favorite political commentators got booted off YT.
-
Is this bad? CJC/IPA heart rate increase 18bpmI experienced an increase in my heart rate of about 18 bpm for roughly 5–10 minutes after injecting CJC/IPA. I’m concerned that this could be indicative of an impending allergic reaction, and now I’m wondering whether it’s safe to start my next vial.
I have one dose left from my current vial, which I will cut in half to see how I respond.
Has anyone had this problem with CJC/IPA but continued it without worsening symptoms?That's totally natural and happens. I get it every time. Indicative that you have good stuff too and your pituitary is responding.
The sudden surge in GHRH causes the heart to beat faster and the flushing feeling. Don't worry or panic, just relax and understand that's just your pituitary spitting out hormones.
Don't cut your dose in half, just continue on. How much are you taking? What was your baseline igf-1 score? Have you had post labs?
-
Are We DumbMaybe, maybe not. I panic bought a horde of bac water a month ago at what is now an absolute steal, and I'm certainly not regretting that purchase.
I stocked up on a bunch of kits as well. I think if it's something you know you're going to use, you've been using it for awhile with good results, and you've got the resources, I'd stock up a little.
-
HGH 191AAMy head is spinning trying to process this info. I am interested in putting the beaver on HGH after watching a few gurus who are touting it. So, can a few of you put down a concise protocol with dosage, peptide stacking, labs to use, gurus with information that you find competent?
I get reluctant when I look at the chemical feedback loops and then it looks tempting to buy one of the guru's time. But with the proliferation of NLP, I know many of them have Tony Robbins plans to siphon as much money off of me as is emotionally possible. So, it would be great to get a plan from some of you who we trust and have used HGH successfully.Start with 1iu. Get labs after 90 days. You want igf-1 ideally between 180 - 220 and glucose <100. Get the basic panel ran as well (CMP/CBC/LIPIDS) just to make sure everything is running smooth. Plenty of lab services online that are cheap.
Look up edema symptoms. Be on the lookout for them, you should be fine at that low of a dosage but still pay attention.
If you get a yearly physical, it would be worth it to schedule during this time, often they run these panels and you can get them for free plus they'll test your BP and benchmark weight.
I do labs twice a year, once for free with my yearly physical and once out of pocket with online services.
Lots of info online. If you're wealthy and have extra resources its worth it to hire coaches/clinics but you can also learn this stuff as well with online resources.
If you run into any serious issues don't hesitate to see your physician and just be up front and honest with what you're doing. They see all sorts of people doing all sorts of things.
-
Discussion: We Left Retatrutide in a Truck All Summer. Then We Tested It.And here’s me covering them up on my desk so the led’s don’t degrade them while I’m playing around with them

Nice test

I've got my peptides stored in a sealed contraption packed in dessicants inside a freezer. Overboard, yes, but they'll be good for many, many years.
Unpopular opinion, but I just have a sneaking suspicion that eventually the crackdown will happen. Hopefully I am proven wrong.
-
Tesamorelin cycling@neil-mccauley do you think 500mcg tesa/250mcg ipa separately w tesa am ipa PM would be a good starting range?
Do them both at same time. Ipamorelin is going to suppress somatostatin tone which will help not only increase the GH pulse from Tesa but also extend the pulse tail, thus resulting in more GH released. Separating them destroys the synergy, and is just more work, more pinning, more supplies, etc.
I'd use a much lower dosage of Ipamorelin to start too. If you have the 10/3 blend, that's going to be 500mcg/150mcg. 150 seems low, but remember receptor saturation point starts at 1mcg/kg, so thats double that amount. If you're pulling them out of separate vials, I'd go 500/100.
Remember, the higher the Ipa dosage the faster/more receptor desensitization will occur (and probably the same can be said about antibody build-up with Tesa). So it really is important to use lower end dosages and use outside methods to help things work synergistically.
This is why I think really being strict about your fasted windows is hugely beneficial (3 hours prior/2 hours after). This will help amplify response and lesson the need for ever increasing dosages. Also, utilizing a 30 day cycle break after 90 days. Exercise is huge, as it lowers fasted insulin/glucose, again, allowing for a more favorable GH response. I think eating a higher protein, less junky carb diet and staying away from all day grazing/snacking and tightening up meal windows with no snacking in between is critical. So is DHEA supplementing if levels are < 300 (improves insulin sensitivity and helps restore GH pulse via several mechanisms).
-
Nexaph User Review: $$$$$My experience with Nexaph was excellent too. Easy to order, website smooth, credit card, free shipping on large orders, shipped fast, responsive customer service inquiry, etc. It was so smooth in fact that it was too easy, in that Nexaph is probably going to end up too successful and get too much attention and get shut down eventually. Which means if you're in need of anything, I'd stock up now while they're still in business.
If there is one positive of the sites that have hoops to jump, middle men, discord and telegram groups and crypto, is that it's too much work for the normies and will fly under the radar. Nexaph seems too good for it's own good in a way, if that makes sense.
-
Nutritional ketosis and fat mobilizing peptidesYou want to pull as many levers as you reasonably (and safely) can. Yes to a lower carb diet. Yes on Tesa. Yes on a GLP.
I would actually advocate for a GLP over AOD for recomp/fat loss if you're looking for something to stack with Tesa. If you already have AOD that's fine obviously use it, remember its 4-6 weeks max before massive desensitization occurs.
If you're new to the GLP game I'd try Tirz first before jumping to Reta. As always, start at the very low dosage. You may end up only needing that.
Remember hormones are the foundation and paramount to keeping fat off long term. Make sure to get a panel ran and that the big ones are at least in a mid range level.
-
Tesamorelin Research Dosing Protocol@jborja said in Tesamorelin Research Dosing Protocol:
Hey friends, @randy might have opined on this also, but curious to hear what others think. I saw another video that nightly tesamorelin might be impacted for those taking Tirz or Reta due to slowed gastric emptying, meaning that folks are not as truly fasted and still carrying heavier insulin when they poke before bed.
I like Tesamorelin/ipa at nights due to restful and deeper sleep (even with toddlers), but I am on tirz and try to have my last bite 3 hours before bed. Not sure if eating dinner 4 hrs before is doable..
Curious to hear your thoughts about a morning routine instead? For you morning folks, do you just wait at least 30 mins before a pre workout? I was gonna try Tesa at night and Cjc in the morning but might be reconsidering this to not have duplicative secretagogues at the same time. Ty!I only research my GHRH/GHRP peptides in the a.m., first thing fasted now, for a whole bunch of reasons. It's just easier and more convenient for me, I know I'm totally fasted with insulin at its lowest point (and therefore getting the strongest amount of receptor saturation as possible).
Plus I'm just more awake/alert in the a.m., easier to pin and reconstitute if need be. I spent many late nights in years past pinning/researching before bed after a long day and when tired, it's just difficult.
I wait 2 hours before eating anything. I drink black coffee right away in the morning after pinning and the combo of peptides, coffee and being fasted in the a.m. is a superpower for getting stuff done. Plus I find GH peptides stimulating in a way in the morning.
I like the idea of going natural at night (no GH peps) and really letting my natural production do its thing. I have found that there must be some carry over anyways, because on cycle my rat sleeps better even though he pins in the a.m only.
Rather than trying to find a way to squeeze in Tesa/CJC in the same day, I'd recommend you use one or the other during your cycle. You can flip flop them as well, going back and forth when one vial runs out.
-
Swollen ankles- side effect?What were your IGF-1 lab markers at? Swollen ankles is a very common side effect of excessively high GH levels. Any tingling feelings in the hands?
What's your blood pressure? What dosage of Sermorelin are you using?
-
Why the Different Strengths?I won’t use a reconstituted vial for more thsn 5 weeks.
Look around here, you will find articles on degradation of peptides after they have been reconstituted. They start to loose they potency….Tirz only dropped from 94% to 92% from day 15 to day 60.
Bac water tested plenty safe at 90 days, and even then its a slow degradation afterwards.
My peptide research is limited to the GHRH/GHRP compounds fwiw. My experience researching them is extensive.
In my lab, I am maintaining a 60ish day window before discarding. I think that's fairly conservative and staying on the safer side without being wasteful and unnecessarily paranoid.
-
Tesamorelin Research Dosing Protocol@jimmy4407th Dial tesa down and be patient. The stuff is is strong even at 1mg. Well for me it is. Water retention, inflammation, tingling... That's you body telling you to chill.
Your body has your best interest. It is constantly keeping you alive regardless what you do to it. Be patient and listen to it.Similar experiences. 1mg is plenty if your pituitary is functional. Especially if you're running Ipamorelin (which you should be) alongside it.
-
Tessamorelin protocol ? Cons / side effects ?@vpeptides said:
@diegoc 200 is not very high, especially looking at your 355. The side-effects seems like settling down.
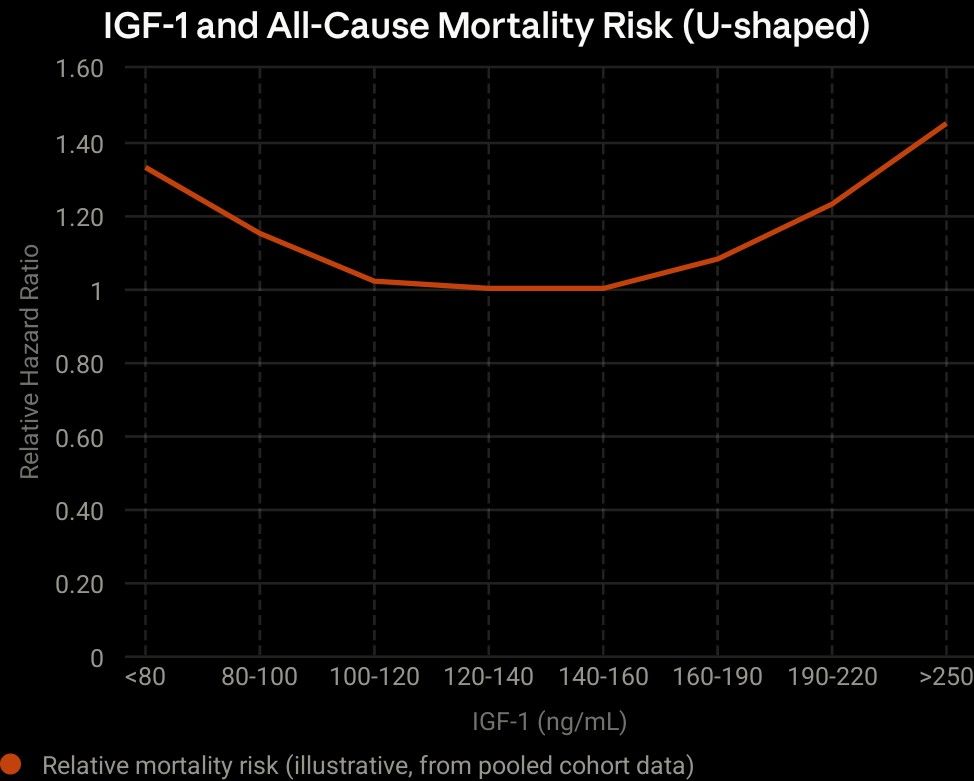
180 - 220 is the sweet spot for long term health and anti-aging. The overall relative risk for all cause mortality starts to increase at 160. I push this a little higher because I find the benefits worth the risk, and given everything else positive I am doing health wise going into the 200 range is fine for me. Personally though would not be comfortable pushing my IGF-1 at 355 long term into older age and beyond, the benefits/risk-reward IMO isn't worth it. 200 is a strong signal and you're getting all the benefits that IGF-1 provides (tissue repair, recovery, lypolisis) while mitigating overall risks.
Going from 121 to 200 on 1mg of Tesa is a solid response. I would add Ipamorelin, if its compounded at 10/3 a 300mcg dose of Ipamorelin is fine, a little on the higher end but should suffice. Retest after awhile and adjust from there.
You might end up only needed 500 -750mcg of Tesa when you combine with Ipa. That would still leave you using 150 - 225 of Ipa which is plenty.
-
Tesamorelin cycling@BeeKind Good question, I wonder how much it can help versus just Tesamorelin. Maybe it can allow to use a lower dose of Tesa, for example instead of 1.5 mg a day use 1.0 mg + 0.2mg Ipa (I just guess the numbers) to get the same IGF1 boost with less Tesa side effects, also a bit cheaper. The trade-off is that you have to make pauses with Ipa.
Your thinking is correct here regarding using Ipamorelin "to get the same IGF1 boost with less Tesa side effects, also a bit cheaper". You need to make pauses with Tesa too (see my responses above about antibody build-up over time).
But I'm with you, I think the doses most are using with Tesa are exceedingly too high. Everyone's basing it on the clinical research using 2mg, but remember, that was based on a sick cohort of users who also were using outdated, less effective methods who needed that kind of dosing to overcome their obstacles. What were they? Multiple comorbitities including HIV, weren't pinning it around fasted windows, didn't pair it with Ipamorelin, and very likely weren't health conscious fitness people.
I suspect that if you correct the mistakes made in the trials with more advanced protocols and a healthier user base, the dosages needed for a favorable response are much, much lower than the 2mg used. Pairing it with Ipamorelin, I'd start with 500mcg and adjust up from there.
-
What's your Favorite Sub Q Syringe ?31g EZ touch from Amazon. They're good for 5 years so I stocked up and you should too, I've got a hunch that they too are going to start disappearing.
Sure, there will be places to procure them online, but not at the current prices.
-
Nexaph testing10% overfill is nice

-
Peptide protocols and resources?You can also use Google Scholar. Many of these peptides have clinical research and data with study participants. I'd suggest reading the data, often very descriptive protocols are given including dosage information.
-
Pulling more than one compound into a syringeAlso don't forget, every time that needle penetrates something, it gets dulled and loses lubricant as well. Bad enough you're using it once to go through a rubber stopper - even worse you're doing that a second time. Hence why peptides that can be injected together, like CJC & IPA, are usually combined prior into one vial.